On 24 February 2013 a Robinson R44 Raven II helicopter operated by Volcanic Air Safaris Limited had just departed on its second scenic flight for the day, with the pilot and three passengers on board, when the engine lost power. The pilot put the helicopter into autorotation and turned the helicopter towards the shoreline, where she carried out a successful ditching in shallow water near the lake edge. The pilot and passengers were able to evacuate the helicopter uninjured. They were picked up shortly afterwards by a nearby jet boat.
Executive summary Tuhinga whakarāpopoto

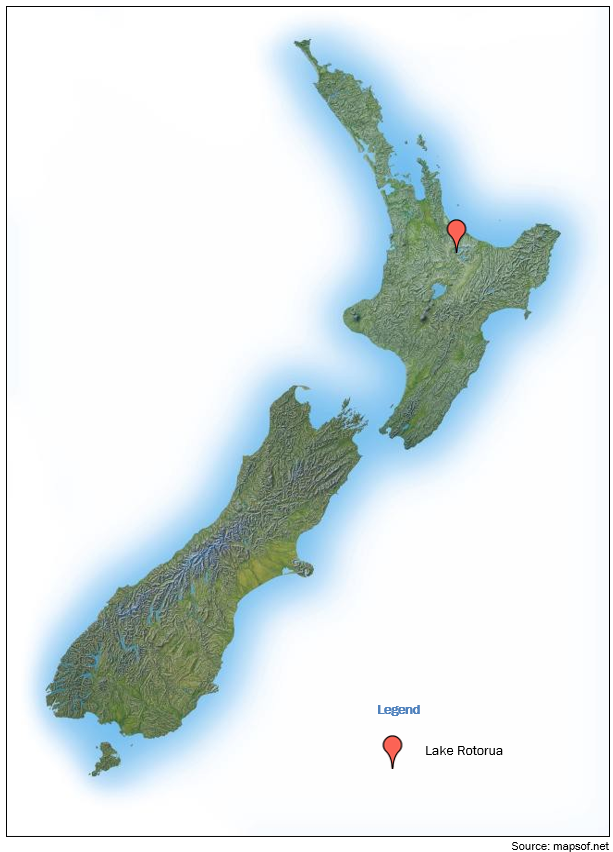
- On 24 February 2013 a Robinson R44 Raven II helicopter operated by Volcanic Air Safaris Limited had just departed on its second scenic flight for the day, with the pilot and three passengers on board, when the engine lost power. The pilot put the helicopter into autorotation and turned the helicopter towards the shoreline, where she carried out a successful ditching in shallow water near the lake edge. The pilot and passengers were able to evacuate the helicopter uninjured. They were picked up shortly afterwards by a nearby jet boat.
- The Transport Accident Investigation Commission (Commission) determined that the most likely cause of the engine power loss was a malfunctioning of the engine’s right magneto. The malfunction was caused by engine oil that had accumulated in the magneto because an oil slinger had been omitted during a maintenance procedure.
- The Commission also found that the imported, second-hand engine and its associated records had not been subjected to the required level of scrutiny before they were released to service, although it is unlikely that this safety issue contributed to the power loss.
-
This report also comments on how the level of risk to people involved in helicopter operations over water, where there is any chance that a helicopter might have to ditch in water, could be reduced if all occupants were made to wear life jackets.
- The Commission made the following recommendations:
- a recommendation was made to the Director of Civil Aviation to provide specific guidance to Civil Aviation Rule Part 145 certified companies, for the performance of conformity inspections of parts and components with unknown service histories or incomplete airworthiness documentation, or that have been stored improperly
- a further recommendation was made to the Director of Civil Aviation to promote the use of quick-donning life jackets for all occupants of single-engine aircraft flying over water
- The key lesson learnt from the inquiry into this occurrence was:
- purchasers of aviation parts sourced without the accompanying proper documentation need to research thoroughly the service histories of the components, as do certifying engineers carrying out the required conformity inspections.
Factual information Pārongo pono
Narrative
- On 24 February 2013 at 0800, the pilot arrived at Rotorua airport and carried out a pre-flight inspection of the helicopter, registration ZK-HAD (the helicopter), checked the fuel load on board and performed a fuel drain check. The fuel on board was approximately 70 litres and nothing abnormal was found during the fuel drain and pre-flight checks. At 0845 the pilot flew the helicopter from the airport to the lakefront helipad, a flight time of about five minutes.
- The helicopter, a Robinson R44 Raven II (R44), was to make two local city scenic flights from Volcanic Air Safaris Limited’s (the operator’s) helipad on the shores of Lake Rotorua, for a family of five. The mother and one child were taken on the first flight, and the father and two children on the second flight.
- The first flight was uneventful, and after offloading the first two passengers back at the helipad, the pilot loaded the other three family members for the second flight. The father and one child were seated in the back, whilst the pilot and one child occupied the front two seats.
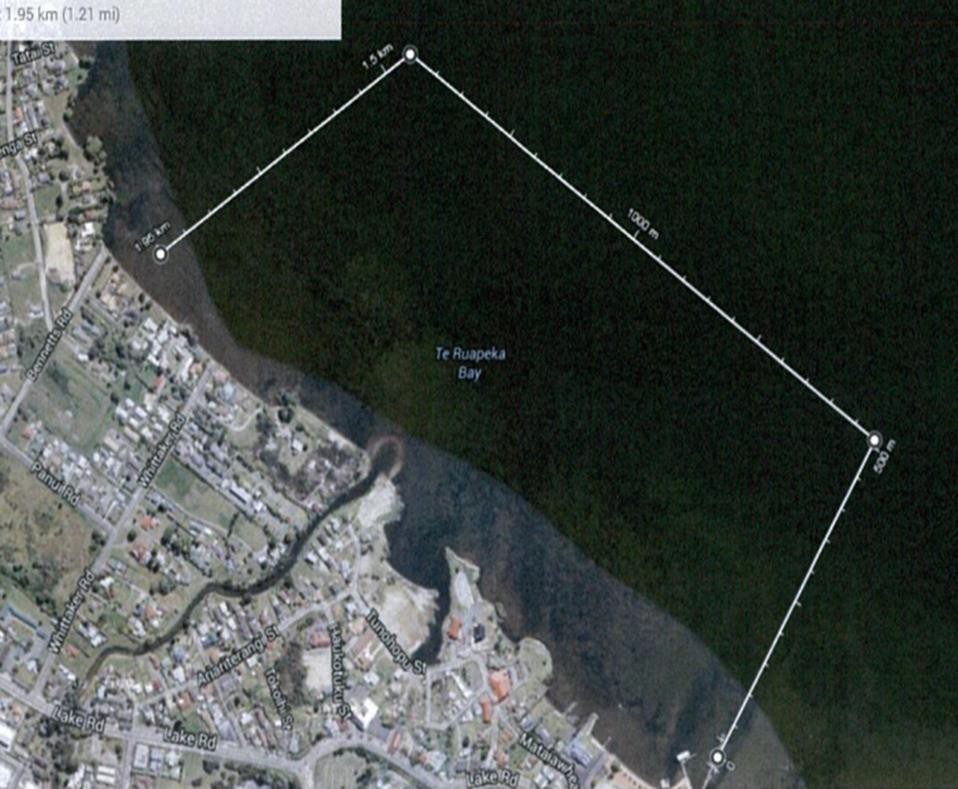
- At about 1009 the helicopter lifted off in an easterly direction, then commenced a climbing turn to the left for an anticlockwise circuit over Rotorua city. After approximately 15-20 seconds, as the helicopter was climbing through 400-500 feet above the lake, the main rotor low revolutions per minute (RPM) warning horn sounded and a strong fuel smell was noticed by the passengers in the rear seat. The pilot checked the instruments and confirmed that both the engine and main rotor RPM indications were decreasing. She then entered the helicopter into an autorotation (a process of producing lift in an unpowered rotor system, by means of inducing an airflow up through the main rotor blades as a helicopter descends). Due to the low height at which the power failure had occurred, the pilot decided not to try to return to the helipad, but to turn towards the lake shoreline and get as close to land as possible. She made a Mayday call (a distress call advising of a condition of being threatened by serious and/or imminent danger and requiring immediate assistance) to the control tower at Rotorua airport, informing the controller that they were ditching (the act of landing an aircraft intentionally with or without motive power into a body of water) in the lake. The helicopter ditched in waist-deep water about 80 metres from the lakefront, on the southern shore of Lake Rotorua.
- The helicopter came to rest with water up to the floor of the passenger cabin. The pilot advised the tower controller that they were safe, switched off the battery and stopped the main rotor turning, then instructed the passengers to evacuate the cabin. The helicopter was fitted with life jackets for everyone on board, and these were stored underneath the seats. The life jackets were not used during the emergency as there was not enough time for the occupants to locate and don them. The pilot took the child seated in the front with her, while the father took the other child. A number of bystanders who witnessed the incident waded out to help. The mother also witnessed the incident from the helipad, and she alerted a local jet boat operator who launched a boat and picked everyone up. There were no injuries to any of the occupants of the helicopter.
Personnel information
- The pilot held a commercial pilot licence (helicopter), which had been issued by the CAA in June 2012. She had qualified to fly the R44 in the same month. She had been hired by Volcanic Air Safaris in October 2012. On 7 November 2012 she had completed a flight crew competency check in the R44, enabling her to carry paying passengers while under supervision. At the time of the incident the pilot’s flying experience in the R44 was 125 hours. She had flown 41 hours and 11 hours in the previous 30 days and seven days respectively, all of which were in the R44.
- The pilot said she had been well rested prior to the duty on 24 February 2013, and had considered herself fit to fly that day. The three days before the day of the incident consisted of a day off followed by a day on call. The day before the incident she had had an eight-hour duty, which included 1.4 hours of flying.
Aircraft information
- The R44 was a four-seat light helicopter, developed from the R22 two-seat model, and had been introduced into service in 1993. The R44 Raven II had first been produced in 2002; it featured an increase in performance over the previous model due to a more powerful fuel-injected engine, and had a maximum certificated take-off weight of 1,134 kilograms.
- The operator had imported the helicopter to New Zealand shortly after it was manufactured, and entered it on the CAA register on 23 October 2007. At the time of the incident it had accrued 2,067 airframe hours. There were no outstanding or deferred maintenance tasks recorded in the aircraft logbooks and it had a valid non-terminating airworthiness certificate.
- The airframes on the R44 model helicopters were required to be overhauled every 2,200 hours of flight time. The Lycoming IO-540 model engine was required to be removed and overhauled every 2,000 hours of flight time, but that interval could be extended by 10% to align with the overhaul requirements of the airframe if the operator flew more than 40 hours per month. The helicopter involved in this incident had not flown that many hours on average, so the engine had to be overhauled at 2,000 hours’ flight time, which became due in January 2013. Rather than overhaul the engine, the operator decided to replace it with a second-hand engine sourced from overseas.
- The replacement engine had 776 total hours logged on it when it was purchased, having previously been installed on another R44 registered D-HPHP in Germany. That helicopter had been involved in an accident in Sweden on 20 June 2011 (Swedish Accident Investigation Authority (SHK) (2012), accident report RL2012:13e, D-HPHP), when it struck the ground and another R44 helicopter while landing. The pilot had been attempting to land in a tight space next to the other helicopter when the helicopter skids dug into the ground and the aircraft rotated uncontrollably. The tail rotor hit the other helicopter and its main rotor blades struck the ground at a high rotational speed. The engine was removed from the wrecked helicopter and listed for sale by a spare-parts company based in Austria. The engine remained in storage for nearly 18 months until it was found by a parts broker based in the United States, who was searching for a replacement engine for the operator.
- The engine logbooks containing the service history of the engine from D-HPHP were included in the sale, but there were no documents to confirm the serviceability of the engine or that it met the airworthiness requirements applicable at the time of the sale. The operator advised that due to this lack of paperwork, and the fact that the engine required a conformity inspection as a result of this, a lower sale price was negotiated. The logbooks contained no record of any maintenance having been undertaken on the engine between the date of the accident in Sweden (June 2011) and when it arrived in New Zealand nearly 18 months later. No evidence was found to confirm whether the engine had been inhibited or preserved (Inhibiting or preserving an engine involves draining the normal operating oil, spraying all the internal surfaces with a special preserving oil, and sealing the engine from the environment) while in storage.
- Because the replacement engine did not come with the required release-to-service documentation, the purchaser was required by the CAA to obtain a statement of conformity from an aviation maintenance company certified under Civil Aviation Rule Part 145, along with an authorised release certificate (also known as a “Form One” (a document that confirms that the part or component to which it pertains is fit for service on an aircraft or aviation component)) before the engine could be fitted to a New Zealand-registered aircraft. The operator engaged Aeromotive Limited to undertake the conformity inspection. The engine and its overseas logbooks were delivered to Aeromotive on 10 January 2013. The engine’s maintenance history and records were checked against the applicable CAA airworthiness requirements. The engine was partially disassembled by removing the cylinders in order to check internal parts against the manufacturer’s design specifications. Cylinder valve guide inspections were carried out on all cylinders.
- A number of additional inspections were required to be carried out before the engine could be issued with a Form One, including an overhaul of the alternator due to its incomplete service history, and a 500-hour inspection of both magnetos (a magneto is a self-contained engine component, consisting of a rotating permanent magnet, field coils and breaker points, which generates the spark at a set time across the engine spark plugs that initiates the combustion of the fuel/air mixture) due to a CAA airworthiness requirement. During the inspection of the magnetos it was recorded in the service paperwork that an oil slinger was replaced on the right magneto. After the required work had been carried out on the engine, and the maintenance organisation’s inspector was satisfied that it conformed to its design specifications, the engine was reassembled and its accessories refitted. A statement of conformity was signed, and a CAA Form One was issued for the engine on 24 January 2013.
- A 100-hour inspection was carried out on the helicopter on 30 January 2013, at 1999 total airframe hours, and the replacement engine was installed. A ground run and test flight were carried out, which revealed rough idling and vibration from the engine. The fuel control unit was removed and sent for repair at Aeromotive. After it was checked and adjusted in accordance with the manufacturer’s instructions, the fuel control unit was refitted to the engine. The helicopter was flown for a further 67 hours until the day of the incident. The last scheduled inspection on the helicopter prior to the incident was a 50-hour check carried out on 21 February 2013.
Post-incident testing and examination
Initial examination
- The helicopter was moved from the lake to Rotorua airport and examined by the two Commission investigators, assisted by two experienced helicopter engineers. The inspection initially focused on the engine and fuel system. The helicopter itself had suffered little damage. The underside of the cabin had suffered water compression dents when the helicopter struck the lake. A tail rotor blade was bent, and the tail rotor driveshaft was broken, when the tail rotor struck the surface of the lake.
- There was no obvious external damage to the engine. Approximately 45 litres of fuel was in the fuel tanks, which would have been enough for about 45 minutes’ flying time. The fuel had the appearance and smell of clean aviation gasoline. The fuel supply and metering system integrity was confirmed, with no leaks under boost pump pressure. The fuel injection system nozzles were free of obstructions and delivered the minimum flow rate as per the engine maintenance manual requirements. The engine control rigging was checked and found to be correct. The oil and fuel filters were free of contaminants.
Fuel control unit
- The fuel control unit was sent to a facility in Auckland, where it was disassembled for detailed inspection and testing in accordance with the manufacturer’s maintenance manual. No defects were found during the inspection. After reassembly it was fitted to a test rig and checked against the manufacturer’s performance specifications. There were two recorded “lean” test points where the unit was supplying less fuel than the specifications, but they were marginally low and unlikely to have caused the loss of engine power experienced during the incident.
Engine testing
- The engine was sent to Aeromotive (Aeromotive operates the only dedicated piston engine test cell in New Zealand) in Hamilton for evaluation and ground operational checks to establish the cause of the power loss. When the right magneto cover was removed to check the breaker and tachometer points, about 200 millilitres of engine oil was found inside the breaker compartment. The oil was drained and the cover refitted with no adjustments made to the magneto. The engine was then fitted and run in the engine test cell. During the initial test run low fuel pressure was observed and the engine ran erratically at low RPM.
- The magnetos were disassembled and visually inspected for defects. Both magnetos were found to have cracked distributor blocks, and the oil slinger was missing from the right magneto. The oil slinger was designed to prevent engine oil entering the contact breaker compartment. A new oil slinger was fitted to the right magneto, and both magneto distributor blocks were replaced.
- The engine-driven fuel pump was found to have a low output pressure, so it was replaced. The fuel control unit was adjusted and a missing induction pipe clamp bolt was replaced. A full engine test run was then carried out with satisfactory results. The engine’s operating parameters were recorded, and were within the manufacturer’s specifications.
Survivability considerations
- The operator had complied with Civil Aviation Rule 91.525, Flights over water, which required that on single-engine aircraft being flown beyond the gliding distance from shore, one life jacket was to be available for each person on board. The life jacket was to be stowed in a readily accessible position.
- The operator’s policy was that pilots and passengers were to wear life jackets on the operator’s longer flights over water, for example to White Island. It was not normal practice to wear life jackets on the short city scenic flights, where most of the flight time was either over land or within gliding (autorotation) distance of land.
- The Commission had previously made a finding in regard to flights that take place in circumstances where the carriage of life jackets are not required by the Civil Aviation Rules, but a ditching was the only viable forced landing option (Report 06-007, Kawasaki-Hughes 369HS, ZK-HDJ, collision with terrain, Mount Ruapehu, 11 December 2006). For example, life jackets were not required to be on board a flight that stayed within gliding (or autorotation) distance of a shore, even if there were no beaches suitable for a forced landing. If at any point in a flight a ditching is likely to have a better outcome than a forced landing on unfavourable terrain, life jackets should be carried. The Commission had recommended in 2008 that the Director of Civil Aviation address this safety issue (recommendation 037/08).
- When established in autorotation, a helicopter will descend much faster than a light aeroplane of similar passenger capacity when established in a glide. Accordingly, the time available to find and don life jackets is significantly less for helicopter occupants than it is for aeroplane occupants.

Analysis Tātaritanga
Introduction
- The Commission found no operational factors that contributed to the incident. The pilot, although not experienced, was appropriately qualified and licensed to fly the helicopter on passenger operations. The evidence showed that it was highly likely that the helicopter experienced an in-flight loss of engine power. The pilot responded appropriately to the helicopter losing power, and made the best of a potentially serious situation by immediately entering the helicopter into autorotation and flying it towards the shallow waters near the lake edge.
- The following analysis discusses the likely cause of the loss of engine power. It also discusses a safety issue regarding the standards of inspection and maintenance of the helicopter’s engine before it was released to service.
- The benefits of aircraft occupants wearing life jackets on flights over water, although not a factor in this incident, are also discussed.
Potential causes of the loss of engine power
- The passengers recalled a strong smell of fuel at the time of the loss of power, and witnesses on the ground recalled hearing “banging noises” from the helicopter. A strong smell of fuel is one indication that an engine is not burning all of the fuel inside the cylinders. In such a case, unburnt fuel can be ignited in the hot exhaust manifold after leaving the engine cylinders, or be distributed into the airflow around the helicopter.
- Fuel igniting in the exhaust manifold can cause backfiring (backfiring in the exhaust manifold is also referred to as “afterfire”), which was probably the loud banging described by witnesses. Another common cause of backfiring in an engine is a problem with the ignition system, such as a weak spark or incorrect timing of the spark. The engine magnetos are an essential component for providing a spark for combustion at the right time. If the timing of the spark is delayed (retarded), backfiring and associated power loss can also occur.
Magnetos
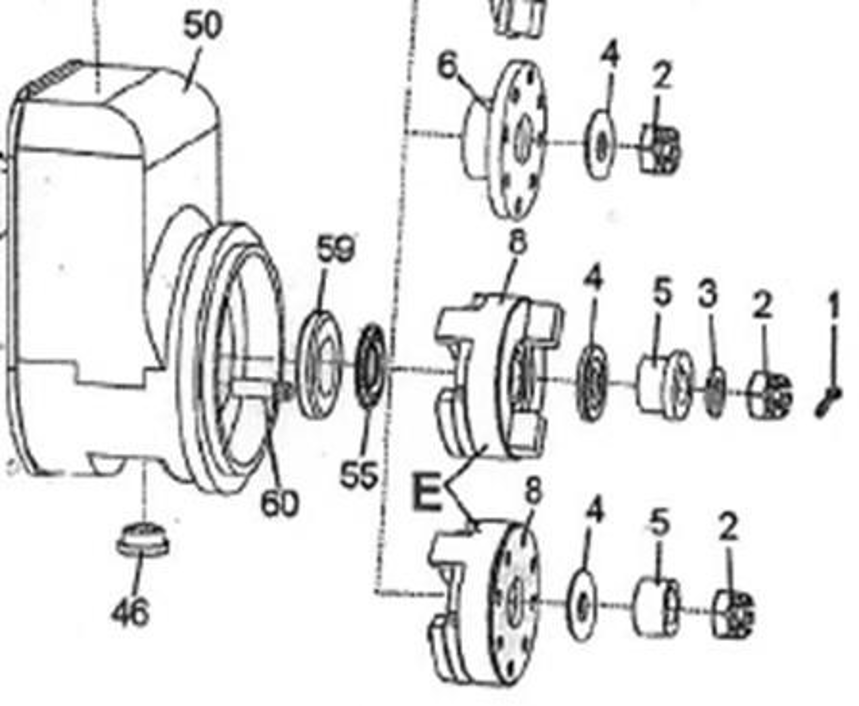
- The magnetos are a self-contained engine component, consisting of a rotating permanent magnet, field coils and breaker points, which generates the spark at a set time across the engine spark plugs that initiates the combustion of the fuel/air mixture. Both the left and right magnetos supply a spark to every cylinder, for redundancy and efficiency. This means that if one magneto is defective, the engine should still run with a reduced power output. When the magnetos were inspected after the incident, both the left and right magneto distributor blocks were found to be cracked. Also, a substantial amount of engine lubricating oil was found inside the breaker compartment of the right magneto.
- A cracked distributer block can affect both the timing and strength of the engine ignition spark, although to what extent is difficult to determine. Distributor blocks are normally reliable and durable. It would be highly unusual for the blocks in both magnetos to develop cracks under normal conditions. For both to develop cracks at the same time indicates that both were subjected to some form of external stress. A sudden stoppage event (when a rotating main rotor blade or propeller that is connected to an engine strikes a solid object such as ground or another aircraft) and damage during maintenance and installation are possible causes. The power loss incident at Lake Rotorua was not considered to be a sudden stoppage event, as the main rotors did not strike the water.
- The oil found in the breaker compartment on the right magneto was more significant. During the conformity inspection Aeromotive had inspected both magnetos in accordance with the manufacturer’s 500-hour inspection schedule. That involved disassembly of the magnetos.
- When the right magneto was reassembled an oil slinger was not refitted to the internal drive shaft that connected the engine-driven accessory gearbox to the magneto. Therefore oil was able to move from the engine-driven accessory gearbox through the magneto and accumulate inside the breaker compartment, which housed the electrical control components of the magneto.
- The level of the oil in the breaker compartment would have risen while the engine was running. Eventually the oil level would have reached the breaker points inside the normally dry compartment. Engine oil does not conduct electricity, therefore the functioning of the contact breaker points that opened and closed, controlling the ignition spark, would have been affected. This would have altered the timing and strength of the ignition spark produced at the associated spark plugs, or prevented a spark being made at all.
- It is highly likely that the timing and strength of the ignition spark produced by at least six out of the engine’s 12 (the engine had six cylinders and each cylinder had two spark plugs, one plug supplied by the left magneto and the other by the right magneto) spark plugs would have been affected by the amount of oil in the right magneto. This would have likely led to a decrease in engine performance.
- A second set of breaker points inside the right magneto sends a pulse signal to the engine RPM governor, which is designed to keep the engine RPM within a certain range. It could have also been affected by the oil in the breaker compartment, which may have caused the governor to change the fuel flow to the engine due to a false RPM signal from the tachometer breaker points. The governor could have been overridden by the pilot opening the throttle, but if she had not done that or that action had not restored power, an autorotation and ditching would have been inevitable. Governor failure was less likely to have caused a sustained loss of power, but it could not be completely ruled out as a potential cause of the initial power loss.
- When considering the amount of oil found in the right magneto after the incident and the effect this would have had on the magneto’s performance, it is highly likely that the omission of the oil slinger when reassembling the right magneto contributed to the engine loss of power. However, other possibilities were considered and are discussed below.
Engine-driven fuel pump
- During post-accident testing at Aeromotive, the engine-driven fuel pump was found to have a lower-than-normal output pressure. Although the output pressure was above the lowest allowable limit, Aeromotive discarded the pump and did not return it to the operator. The engine-driven fuel pump that was fitted to the engine had been subject to an earlier mandatory service bulletin issued by the manufacturer, Lycoming, in 2005. Certain pumps made during a short period in 2001 had been found to have been manufactured outside the specifications, which could result in a restricted fuel flow. No record of the service bulletin having been carried out on the pump could be found in either the overseas logbooks or the records for the conformity inspection conducted by Aeromotive. The date of manufacture of the pump was marked as a date code on the pump itself, but, because the pump was disposed of, the Commission was unable to determine whether it had been one of the potentially defective units.
-
The Commission contacted Lycoming to try to establish through its records whether the pump installed on the engine at engine manufacture had been affected by the service bulletin, as it was the same pump fitted at the time of the incident. However, Lycoming said that it had not recorded the date the pump was made or the engine on which it had been installed.
- Given that the fuel pump was found to be still delivering fuel pressure above the minimum allowable limit, it is unlikely that it would have caused the loss of engine power. Nevertheless, it is concerning that there was no record of Lycoming’s mandatory service bulletin ever having been carried out. This is discussed further in the following sections of this report.
Fuel control unit
- There was no record of the fuel control unit having been disassembled, inspected or tested during the conformity inspection. However, it was checked as being the correct type for the engine model. The engine and its components were released to service and subsequently fitted to the helicopter. After initial ground runs of the engine, the fuel control unit was sent back to Aeromotive due to rough running and an unsatisfactory flight check. The unit was checked and adjusted to within specifications. At that time Aeromotive carried out a CAA airworthiness directive (a mandatory airworthiness requirement that specifies modifications, inspections, conditions or limitations to be applied to an aircraft or aeronautical product to ensure continued safe operating conditions) (DCA/MA/16) on the fuel control unit. The directive should have been carried out as part of the conformity inspection, before the fuel control unit was first released to service. The fuel control unit was then refitted to the helicopter and no further problems were recorded with the engine until the power loss event. During flow testing after the incident, the fuel control unit was found to be marginally “lean” at two test points. It was then disassembled and adjusted, and the stem seal and adjustment nut were replaced inside the servo chamber.
- It is not likely that the fuel control unit contributed to the loss of power. It had been operating satisfactorily up until the incident, and the post-incident testing did not reveal any significant defects. However, as with the engine-driven fuel pump, it is of concern that a CAA airworthiness directive had not been carried out on the unit during the conformity inspection prior to the engine being released to service.
- In July 2014 the CAA issued an Airworthiness Directive (DCA/MA/17, 11 July 2014) for fuel control units installed on R44 II helicopters. It was prompted by an incident in February 2014 involving an R44 II that lost engine power and had to carry out an autorotation landing. The directive required all units to be disassembled and inspected within five hours’ flying time or 200 hours’ total time in service (whichever was the later), to check for delamination of a Teflon washer inside the unit. Several units, including the one involved in the incident in February 2014, had badly delaminated washers that had led to material separating from the washers, and one had partially blocked the fuel metering system at a fuel injection nozzle. The fuel control unit installed on the helicopter at the time of the loss of engine power had been exchanged for a new unit when the engine was overhauled in November 2013 (when the operator was made aware of the engine’s sudden stoppage event of 2011, it had the engine overhauled and the fuel control unit replaced). Although the unit could not be traced by the manufacturer, the fuel metering system was checked for blockages during the post-incident inspection. All of the fuel nozzles were removed for inspection and their flow rates were checked in accordance with the engine manufacturer’s instructions. No defects or obstructions were found and the flow rates were equal and within the specified limits. A blockage in the fuel metering system was very unlikely to have been the cause of the loss of engine power.
Inspection and maintenance
- There is a degree of risk when second-hand engines and engine parts are purchased, particularly when the parts are sourced from overseas, outside the New Zealand civil aviation system. The CAA has issued guidance in the form of Advisory Circular AC 00-1 for owners and operators who purchase used parts from overseas. The advisory circular stresses the importance of sourcing used parts from reputable organisations and ensuring that proper and complete paperwork is provided to confirm the parts’ airworthiness status. It also warns that salvaged parts may be passed off as serviceable and that there should be suspicion of any parts that do not have the correct documentation.
- In this case the engine that was fitted to the helicopter had been offered for sale by Euram, a used aircraft parts dealer based in Austria. There was no accompanying documentation to reflect its airworthiness status. There were two documents supplied by the dealer together with the original logbook. The logbook covered the entire period of the service history of the engine. One of the documents was a removal certificate, which stated that the engine had been removed from an R44 helicopter and had not been exposed to fire, water or extreme stress. A second document was a material certification that recorded the engine part and serial number, as well as the helicopter from which it had been removed. The second document stated that the engine had not been subjected to fire or water. It did not mention whether it had been exposed to extreme stress. Neither document was dated, nor was there a document number or purchase order number recorded. The sale documents did not include a “removed unserviceable” tag or any other information about why the engine had been removed. Similarly, no such information had been recorded in the engine logbook.
- The company that carried out the conformity inspection (Aeromotive) had been made aware of the engine’s involvement in an accident overseas. The purchaser (Volcanic Air Safaris) told Aeromotive that the engine had not been running at the time of the accident. Volcanic Air Safaris had been given this information by the parts dealer, who indicated that the helicopter in which the engine had been installed had been parked on the ground when it was struck by another helicopter attempting to land nearby. Neither the operator nor Aeromotive made enquiries to confirm the details of the accident with the previous owner, nor did they question the lack of information about the accident in the engine’s logbook and accompanying documents.
- After an online search of an international accident database, the Commission found the full details of the accident as well as the publicly available report into the accident completed by the Swedish Accident Investigation Authority. It was clear from the factual information in the accident report that the engine had come from the helicopter that was attempting to land, and that the engine had been running and therefore subjected to a sudden stoppage event.
- The manufacturer’s maintenance instructions directed that following a sudden stoppage the engine was to be disassembled, paint-stripped and closely examined for damage using non-destructive testing methods. The engine accessories, including the magnetos, were required to be examined for damage. There was no evidence that this procedure had been carried out either before or after the engine was removed from the helicopter and listed for sale. Aeromotive was not given, and did not seek, detailed information about the accident in Sweden. Consequently the procedure was not carried out by Aeromotive in New Zealand before the engine was released to service.
- Engines that are not used for periods of more than 30 days are prone to component deterioration, caused in part by the accumulation of moisture within the engine. In such cases the engine manufacturer recommends that an engine be preserved or inhibited to protect it and its associated components from deterioration. No records could be found to confirm whether the engine had been inhibited in the 18 months that it was stored before being sold to the operator. This process normally involves draining the normal operating oil from the engine, filling it with special preserving oil, installing moisture-absorbing desiccants and sealing the engine from the environment. If this is not done prior to long-term storage, corrosion can develop on exposed parts, and seals and diaphragms in the oil and fuel systems can deteriorate over time.
- As part of the conformity inspection the logbooks and original export certificate of airworthiness issued in the United States were reviewed to confirm the engine’s origin and service history. The engine was also partially disassembled to access the inside of the crankcase, and various parts and components were evaluated against the manufacturers’ approved type design data. The engine and its accessories were not functionally checked during the conformity inspection, or prior to the issue of the Form One.
- The Commission checked the service history of the engine against the CAA airworthiness requirements and the manufacturer’s instructions for continued airworthiness. Aeromotive had not recorded the manufacturer’s mandatory service bulletins that had been carried out, or checked as having already been carried out, during the conformity inspection. Two service bulletins issued by the manufacturer of the magnetos had been required to be carried out, but there was no record that they had been, prior to the magnetos being released to service. One of them (Service Bulletin TCM SB658) related to inspecting the distributor gear. The other (TCM SB663A) was for an inspection of the tachometer (governor) breaker points inside the right magneto.
- The standards of maintenance and inspection for the import and eventual release to service of this helicopter engine cannot be considered to have met the standards of aviation maintenance best practice. The Civil Aviation guidelines (AC 00-1) for importing aircraft parts from overseas and determining their acceptability had not been followed. The engine’s history and the lack of appropriate accompanying documentation meant it should have been subjected to more rigorous inspections. At least four manufacturers’ mandatory service bulletins for engine components had not been recorded in the engine’s logbook as having been previously carried out, and they were not carried out by Aeromotive before the engine was released to service.
- The CAA released Advisory Circular AC 00-1 to assist purchasers and installers of aircraft parts in identifying parts that were unacceptable to use on type-certificated aircraft. It emphasised the need to assess the accompanying documents for errors and omissions, and to be wary of certain indicators of suspect parts, such as low prices and incomplete service histories. The guidance also stated that purchasers should aim to ensure complete traceability and quality, and that they should not place installers in the position of accepting responsibility for unacceptable parts.
- However, a purchaser may not be able to establish the quality of a part if they are buying from overseas, and will not necessarily be familiar with the accompanying documentation and maintenance records that provide traceability.
- In this case there was no release certificate accompanying the engine when purchased, which meant that it had to be sent to an aviation maintenance organisation certified under Civil Aviation Rule part 145 for a conformity inspection in order to have a release certificate issued. This had to be done before it could be installed in a type-certificated aircraft in New Zealand. In accordance with AC 00-1, the ultimate responsibility for accepting the part was on the installer. However, in this case, when the engine was received by the installer it had already been through a conformity inspection and issued with a release certificate by a Part 145 company. This document, also known as a Form One, stated that it was fit for service and eligible for installation. Therefore the company certifying the conformity inspection, which was aware of the engine’s involvement in a previous accident overseas, had the greatest responsibility for ensuring the acceptability of the engine before issuing the release certificate.
- The CAA had issued guidelines (AC 145-1) for Part 145 companies, which listed the procedures that should be included in a conformity inspection for an item of unknown origin. These procedures involved inspecting the item for conformity to specifications, drawings, dimensions, type of material and state of preservation. The guidelines also required an assessment of the item’s airworthiness status, including Airworthiness Directives and the traceability of life limits, and a functional test if applicable. The guidelines did not specify what was to be done if the state of preservation was substandard, the service history was incomplete or the accompanying documents were incorrectly completed. They also did not explain when functional testing was required to be carried out, and what it should entail. The guidelines did not differentiate between a new item and a used item, or state which specifications, design or performance, should be checked. It was up to the Part 145 company to develop its own procedures from the guidelines and decide on the levels of disassembly, inspection and functional testing required for each conformity inspection.
- The CAA had not released training material specifically for engineers who carried out this type of conformity inspection, and it was left up to the Part 145 companies to train their staff in the procedures involved. Part 145 companies routinely relied on the training provided during CAA-run Inspection Authorisation courses to educate their staff on the procedures. However, this type of conformity inspection was not covered during the Inspection Authorisation course. In this case, the procedures used during the conformity inspection did not ensure that the engine was acceptable for installation. This suggests that the CAA should issue further guidance to Part 145 companies for carrying out this type of inspection.
- The engine loss of power was most likely to have been caused by the oil in the right magneto, which was the result of a simple maintenance error. If this was the case, the non-adherence to CAA guidance and the failure to perform mandatory service bulletins were unlikely to have contributed to the engine power loss. Nevertheless, similar standards of inspection and maintenance could result in accidents and incidents in future unless the standards are improved.

Wearing of life jackets
- A major power loss when departing from or returning to a shore landing site can lead to a ditching. A less-controlled ditching, or a ditching into deeper water, could have had a less favourable outcome in this incident. The operator had complied with the regulatory requirement for the carriage of life jackets, but the occupants were not required to wear them under normal circumstances. After entering autorotation the pilot did not instruct the passengers to don their life jackets, and being at a low height there was very little time for them to have done so before the ditching.
- There is now a wide range of life jackets available that allow quick donning. For example, the pouch-type jacket is secured to a person by a belt. The jacket can be pulled out of the pouch and put over the head as soon as a need is indicated, and activated once clear of the aircraft. A life jacket of this type would have been appropriate for the operator to have provided and, as discussed below, required to be worn on flights operated from the lakeside base. The Civil Aviation Rules prescribe the minimum safety requirements. Operators should anticipate the risks that are specific to their operations and plan adequately for them.
- The Commission has an open safety recommendation, made to the Director of Civil Aviation, concerning the carriage of life jackets on flights where a ditching is likely to have a better outcome than a forced landing on unfavourable terrain (recommendation 037/08). That recommendation recognises that an aircraft could be within gliding (or autorotation) range of a shore and therefore not required to be equipped with life jackets, but if the shoreline is hostile and does not afford a reasonable landing site a ditching could be inevitable. Therefore, it would be sensible for life jackets to be carried.
- The present incident is a reminder that much less time is available for helicopter occupants to find and fit their life jackets than there is for aeroplane occupants faced with a ditching from the same height. The Commission is recommending that the Director of Civil Aviation act on the earlier recommendation by encouraging operators of single-engine aircraft flying over water to use quick-donning life jackets when a ditching is the only or the preferable forced landing option. This is particularly warranted in situations where a ditching could be carried out with little notice, such as in a single-engine helicopter, when insufficient time is available to don a standard life jacket before entering the water.

Appendix 1. Magneto diagram